Coronavirus Impact III

That the US government pays additional money to the entity providing care an amount substantially more than if they did not die from covid.

Can you evidence that?


A reason flu deaths are down is because people who may otherwise have died of "seasonal" flu are instead dying of COVID.

So yes, flu deaths are down at least in part due to COVID deaths.

Another reason, logically, is that people are afraid to go into a doctor and as a result fewer flu cases are made known to the medical community. But that is only speculation on my part.

So what happens when / if we get to where productions won't hire you unless you've had the vaccine? The Boomers get all the jobs as a result of the 5D kids being the last on the list for vax? :happy:
 
I charge my clients more due to COVID restrictions and safety measures and its impact on production. You should also.

Sometimes the rate is the rate, you are competing with others willing to do the job for that rate, and you either take it as is or decline. They'd laugh if you demanded some sort of COVID-bonus. Yeah, like that's happening. That and a bonus for having to work a holiday.
 
Can you evidence that?


A reason flu deaths are down is because people who may otherwise have died of "seasonal" flu are instead dying of COVID.

So yes, flu deaths are down at least in part due to COVID deaths.

Another reason, logically, is that people are afraid to go into a doctor and as a result fewer flu cases are made known to the medical community. But that is only speculation on my part.

So what happens when / if we get to where productions won't hire you unless you've had the vaccine? The Boomers get all the jobs as a result of the 5D kids being the last on the list for vax? :happy:


It is part of the massive Covid relief act passed late last March or early April to help hospitals and any care-giving entities to cope with the load of patients and the need for special care - PPE and all other unique requirements. I do not know the amount or if it varies by case, but it does stipulate special payments for covid deaths.
 
does stipulate special payments for covid deaths.

No it doens’t.

The cares act provides a 20% bump for Covid related treatment billed through Medicaid, as in, not for deaths but for all treatment of anyone presenting with a Covid diagnosis. Also to cover those that aren’t insured.

You know I didn’t know the amount or that this was the case, but I found it in about 60 seconds. Why can’t you check BS like this before you post it ? It’s so easily checked. This is straight out conspiracy disinformation.

https://www.aha.org/news/blog/2020-...eal-so-financial-strain-life-saving-hospitals

“ The truth is, hospitals and health systems are in their worst financial shape in decades due to the coronavirus. In some cases, the situation is truly dire. An AHA report estimates total losses for our nation’s hospitals and health systems of least $323 billion in 2020. There is no windfall here.”

https://www.factcheck.org/2020/04/hospital-payments-and-the-covid-19-death-count/
“ As for the accuracy of the death toll, other experts have previously told us that while it’s true that some deaths attributed to COVID-19 likely would have occurred regardless of the disease, other factors — like the deaths of undiagnosed COVID-19 victims, including those that occur at home — contribute to a more significant problem of under-counting the deaths.”

If there was accounting errors then why the hell have a few hundred thousand extra Americans died this year ?

(From Nov 9)
“According to the Centers for Disease Control and Prevention, there have been as many as 299,028 more deaths this year compared to a typical year (as of Oct. 15, 2020). There have been 216,025 deaths due to COVID-19. There is no reasonable explanation for the increased deaths other than COVID-19.“
https://www.aha.org/news/blog/2020-...lse-claims-about-covid-19-deaths-and-payments

If anything the number of people dying from Covid is underreported...
https://jamanetwork.com/journals/jama/fullarticle/2771761

“ Previous studies of excess deaths (the gap between observed and expected deaths) during the coronavirus disease 2019 (COVID-19) pandemic found that publicly reported COVID-19 deaths underestimated the full death toll, which includes documented and undocumented deaths from the virus and non–COVID-19 deaths caused by disruptions from the pandemic.”

We can do better than posting conspiracy theories like this can’t we ?

JB
 
Last edited:
No it doens’t.

The cares act provides a 20% bump for Covid related treatment billed through Medicaid, as in, not for deaths but for all treatment of anyone presenting with a Covid diagnosis. Also to cover those that aren’t insured.

You know I didn’t know the amount or that this was the case, but I found it in about 60 seconds. Why can’t you check BS like this before you post it ? It’s so easily checked. This is straight out conspiracy disinformation.

https://www.aha.org/news/blog/2020-...eal-so-financial-strain-life-saving-hospitals

“ The truth is, hospitals and health systems are in their worst financial shape in decades due to the coronavirus. In some cases, the situation is truly dire. An AHA report estimates total losses for our nation’s hospitals and health systems of least $323 billion in 2020. There is no windfall here.”

https://www.factcheck.org/2020/04/hospital-payments-and-the-covid-19-death-count/
“ As for the accuracy of the death toll, other experts have previously told us that while it’s true that some deaths attributed to COVID-19 likely would have occurred regardless of the disease, other factors — like the deaths of undiagnosed COVID-19 victims, including those that occur at home — contribute to a more significant problem of under-counting the deaths.”

If there was accounting errors then why the hell have a few hundred thousand extra Americans died this year ?

(From Nov 9)
“According to the Centers for Disease Control and Prevention, there have been as many as 299,028 more deaths this year compared to a typical year (as of Oct. 15, 2020). There have been 216,025 deaths due to COVID-19. There is no reasonable explanation for the increased deaths other than COVID-19.“
https://www.aha.org/news/blog/2020-...lse-claims-about-covid-19-deaths-and-payments

If anything the number of people dying from Covid is underreported...
https://jamanetwork.com/journals/jama/fullarticle/2771761

“ Previous studies of excess deaths (the gap between observed and expected deaths) during the coronavirus disease 2019 (COVID-19) pandemic found that publicly reported COVID-19 deaths underestimated the full death toll, which includes documented and undocumented deaths from the virus and non–COVID-19 deaths caused by disruptions from the pandemic.”

We can do better than posting conspiracy theories like this can’t we ?

JB


First up, they do pay more for covid, and that is all I said. I also indicated that I have no idea if this policy affects the official numbers one way or another.

from the medicaid.gov website - as of January of this year 77,000,000 plus people are in Medicaid and CHIP in the US as of Sept of 2020 (that is a lot of people and unfortunately, they are also more vulnerable.)

from HSS website (Note the bold is my emphasis) - https://www.hhs.gov/coronavirus/cares-act-provider-relief-fund/for-patients/index.html

"Private insurers generally must waive an insurance plan member's cost-sharing payments for COVID-19 diagnostic testing and certain related items and services.

Some private insurers, including Humana, Cigna, UnitedHealth Group, and the Blue Cross Blue Shield system, have agreed to waive cost-sharing payments for COVID-19 treatment for insured patients."

This means there are many other entities receiving support from the government for providing covid care.


The point of this is not the specific numbers or if there is a conspiracy, but the added payments create an atmosphere for potential conflict. If my words to you seemed to indicate more, I apologfize - that was not my intent. BTW, the three doctors I know all have had several circumstances where they were pressured to change the death certificate to covid from another reason. Small data point I know, but a cause for suspicion.

Lastly, this whole covid thing is, in itself, the most confusing and debilitating mess of my lifetime and only a few countries have gotten it mostly right. If you live in one where it has gone well, consider yourself fortunate. Even if the vaccines do their job (looks promising if we can get them out) the economic mess will be with us for a decade or more in all likelyhood. I know my business likely will not survbive the year, but it won't stop me from trying to forge forward. Best of luck to you.

B
 
I'm sorry to hear your business might not survive the year, B. Here's hoping that things turn around quickly. Some economists predict a quick rebound after the pandemic ends because even though physical workers have gotten hammered, computer workers have by and large done just fine (not to mention the stock market) and should be ready to spend their savings once things open up, effectively stimulating the economy. (Someone mentioned to me recently that you couldn't get a baseball ticket the year after the Spanish flu ended because demand was so high.)

Regarding the covid count in the US - if there is an error, I would bet that the error is marginal and I wouldn't be sure if it's an over count instead of an undercount, even if hospitals are misattributing deaths.

But there has been such a streak of covid denialism in the US that any suggestion of systematic deception feeds into that notion, which I strongly object to.

The larger issue, in my view, is that the businesses and workers who have been asked to close up shop have not been adequately compensated, and so the costs have fallen disproportionately on them and it's simply unfair. Many of those folks make less money than computer workers, and so the working class has suffered and fallen behind while the upper middle class is doing fine.

On the point of profit-driven medicine in the US - it is a big problem. My dad was a neurologist and told me stories of people conducting harmless but unnecessary tests to pad their insurer bill. One doctor bought his own million-dollar machine (eeg? Cat scan? I can't remember.) Normally those machines are rented, and the bulk of the payment went to the supplier. But now he was minting money with it and lots of people had a scan who didn't really need one.

Some of that fraud may have been rooted out by now. But hospital administrators are always keen to maximize profits and minimize costs. It's hard to police doctors when you dont understand what they're doing and you dont want to risk your life on it. Meanwhile, you dont pay the costs directly as they go to the insurer, which grossly inflates the cost of medicine in the US.
 
David Leonhardt tweets:
I just took a 1,600-mile road trip from Washington to St. Louis and back. I was shaken by what I saw.
Almost everywhere I stopped — gas stations, rest stops and hotels, across Maryland, West Virginia, Pennsylvania, Ohio, Indiana and Illinois — there was a sign on the door saying that people had to wear masks to enter. And almost everywhere, most people ignored the sign...
Nationwide, about half of Americans are not wearing masks when in close contact with people outside their households, according to a survey by the University of Southern California.
https://twitter.com/DLeonhardt/status/1352596455450701828

I understand the resistance to lockdowns because people blame the lockdowns for harming their livelihoods instead of blaming the virus itself (which I think is a mistake), but I really, really don't understand the resistance to masks.
 
David Leonhardt tweets:

https://twitter.com/DLeonhardt/status/1352596455450701828

I understand the resistance to lockdowns because people blame the lockdowns for harming their livelihoods instead of blaming the virus itself (which I think is a mistake), but I really, really don't understand the resistance to masks.

I live in MD (so cannot speak to any other state) and you cannot get inside anywhere without a mask. Been that way for more than ten months now. And I agree, while masks are not complete protection for anyone, they do slow things down quite a bit. I don't get the resistance to them either.
 
Indiana is pretty spotty as far as mask wearing. “No shoes, no shirt, no dice”, unfortunately the Spicolli rule is rarely enforced. Come in with mask on and take it off in store. Early in spring some had mask wranglers offering masks , some occasionally with law enforcement. Don’t see officer’s in six months at entrances.
 
First up, they do pay more for covid, and that is all I said. I also indicated that I have no idea if this policy affects the official numbers one way or another.


That’s not what you said.

In the context of a discussion about the numbers of COVID deaths being very high in the US, there’s a theory that the deaths rate is artificially high because doctors are bumping deaths (from say Flu) that would have happened anyway to being due to Covid because they get paid more.

You actually wrote

...I do not know the amount or if it varies by case, but it does stipulate special payments for covid deaths.

And that’s just not true.

YES. Any medical treatment that is COVID related gets billed with a 20% bump. That’s what is actionable and billable.

But it’s any treatment.

That’s a very different thing to getting a special payment for a Covid death. It’s not a payment for DEATH. It’s a 20% bump on what they would get paid anyway NO MATTER IF THEY LIVE OR DIE. It also presupposes widespread fraud on behalf of the medical personal.

I also have many friends in medicine. I worked on a series that was literally about medical malpractice and the bad behaviours of doctors and hospitals and the culture of covering up those errors.

The main premise of the show is a startling fact. Medical error appears to be the third leading cause of death in the US.
https://www.hopkinsmedicine.org/new...rs_now_third_leading_cause_of_death_in_the_us

“ The researchers caution that most of medical errors aren’t due to inherently bad doctors, and that reporting these errors shouldn’t be addressed by punishment or legal action. Rather, they say, most errors represent systemic problems, including poorly coordinated care, fragmented insurance networks, the absence or underuse of safety nets, and other protocols, in addition to unwarranted variation in physician practice patterns that lack accountability.”

We did episodes on up-coding, where you “work” the billing system to use higher paying codes to make more money. One episode was based on a true case where a patient came in for a procedure and dies of an unrelated illness in the hours before the procedure. They still performed the now unnecessary procedure on the now dead patient so they could still bill for it. The main medical advisor on that series once said to me, the difference with the US medical system is that many doctors get paid per procedure. Most of the rest of the world, the doctors are on a salary. In her words....

”...its like paying cops for every ticket they write...”

This kind of fraud though is actually very rare. Most of the time the medical errors are genuine errors because someone is trying to save your life and makes the wrong call.

This conspiracy theory of high Covid numbers in the US being due to billing deaths that would have happened anyway to Covid is what I am calling out. So if that’s not what you’re claiming then all fine, but I have several friends that work in ER and have been working in actual frontline Covid wards and I specifically asked them about this and they literally get angry and shake with rage.

It’s medical fraud. It’s against HIPA. Anyone of them caught doing that would instantly loose their ability to practice and they just wouldn’t do it. And did I say how it enrages the very people trying to keep us alive that we’re buying this theory ?

The real issue here, and last time I brought this up the thread got closed so I say it as lightly as possible......is public health. It’s a cultural issue about how we treat public health.

This is a “public health” issue.

That means the public have to take it seriously. It’s like arguing that you have a right to go inside a shop or fly on a plane and smoke. Or to smoke at work because your freedoms are violated if you don’t allow that choice. Do we tolerate that ?

We all accept that for the good of those around us, you’re not permitted to, usually enforceable by law. Sure you can do it at home, or in a park somewhere outdoors not too close to others.....

The countries that have much lower infection rates and death rates with Covid are the ones that have leadership that defined the issue, listened to science and didn’t turn this into an issue of personal freedoms and choice. They took the economically painful choices early and now they’re reaping the benefits of very low inflection rates.

Muddying the waters and giving oxygen to theories about Covid not being as terrible because the numbers might not really be that high and = many of these people were going to die anyway is self centred thinking.

Look at the numbers. Hundreds of thousands of EXTRA Americans died in the last 12 months. They would NOT have died anyway. They’re extra...way above norms....

I just want to counter anyone who want’s to argue that it’s some kind of numbers fudge. I have too many friends that have suffered already.

I have great optimism on the work front. I hope your buisiness survives and that you’re able to access any support you can to stay afloat. I think the economic impact will be long lived, but the need for content hasn’t diminished. I hope that turns into a boom for you and your business.

JB
 
Last edited:
John, you are presuming the administrative rules for filing to get the additional money are exactly the language in the legislation and those rules and the forms to substantiate the validity of the claim are often quite different from the legislative language. It is in those details that the stories about coercion to change information (on death certificates for one) probably get their roots. The best illustration to this is the small business loan program to help to keep employees at work. It was supposed to be simple. It wasn't. Since I am self-employed, I did not qualify for that program, but several of my clients did. Over 8 weeks the administrative guidance given by the IRS to the banks changed weekly. One of these businesses had to refile 5 times before finally meeting the requirements. And now, when it is time to go through the "loan forgiveness" process, those regs have changed four times as of last week. And this small biz stuff is easy - as in not life and death. In the medical field I can see them changing weekly (if not daily) and listing the death as covid is likely one of the requirements in many of the circumstances. Hence my use of the language that I used. All I know is this one giant cluster.......

I have never said I think the numbers are inflated. There is not doubt about the magnitude of the problem. I am trying to point out that where there is smoke there is reason to look deeper and I have an innate skepticism about information that is not yet fully vetted and withstood the test of long term analysis. We are still getting revisions on data interpretation on a monthly, even weekly, basisi.

As for open information, I think few states have tried as hard as MD and yet the numbers they publish just do not make any sense. I don't distrust them, but I cannot see their value. For me they cause more questions than they answer - (link here - https://coronavirus.maryland.gov/ )

For example, there are about 6 million people in MD. Since early last March (published at 10AM on Saturday morning) 339,307 people have contracted covid (increased of 2392). Persons tested negative 2,771,726 11,008 in the prior 24 hours). Testing volume at this point is 6,678,255, an increase of 47,692 (and more than 600,000 more than the population of the state - BTW, neither I nor my wife have been tested). Percentage testing positive (Positivity Rate) 7.39% (down 0.11). Confirmed Deaths 6662 (plus 45 over the previous 24 hours). Currently hospitalized 1,717 (down 51 over previous 24 hours).

Now on the surface this all looks dandy, but over the weeks (besides the enormous amount of testing) the one truly odd stat is what happens to all the testing info. Note total tested: 47,692; tested negative 11,008; tested positive 2,392. what about the other 34,292? This has been going on for weeks/months. There is never any seeming rational continuity to the numbers and they never add up nor are they reconciled. And there is no explanation.

So I appreciate that you think you have the right approach on this, but from my perspective, you are far too accepting of info that has not been vetted at all - none of it has, so please forgive my skepticism and my willingness to question.

I too wish you well, but you may want to rethink your need to attack valid statements just because they do not sound right to you. And I will try to be far clearer in my intent. Peace and Godspeed!

B
 
Just to double down on what John is saying -

The treatment for flu is different from the treatment for covid. If you don't test your patient to find out what they've got in order to provide the correct treatment, you're opening yourself up to a malpractice lawsuit.

If they test positive for flu but not covid and you write them up as a covid patient, the government Medicare auditors will find out in your paper trail and will charge you with fraud.

The same goes for if the patient dies and you report it as a covid death when they tested negative for covid.

The financial risks of malfeasance are so much greater than the rewards.

The only reason they are plumping up the Medicare payments is because Medicare pays much less than private insurers and they don't want hospitals to turn these patients away. We're not talking about a big payday here. In fact, many hospitals are now losing money despite the massive influx of business (ie patients) because they make more money from expensive elective surgeries than they do from treating common ailments.

Of course you must test and you must know what and how to treat. (I wonder if there are any flu cases at all at this point). And you are so right that these types of treatments do not pay like all kinds of elective and non-time critical procedures. And they may not be getting rich (far from it) but we will likely never know the real circumstances we are all discussing.

There was an article about two of the hotspots - one in TX and one in CA - late last week or early this week. I am not quoting what I read, but many of the hospital facilities were so overwhelmed that they could not take heart attack and stroke patients - an unintended complication from the approach (or lack of one) that has been taken (about 50 different approaches - states - only a few of which have seemed to work at all).

In the first four-five months of this mess - in MD - they were only testing folks with respiratory symptoms and fairly sick at that. It was astounding to see then that less than 15 percent of the people tested actually tested positive for covid. This was before masks were being used as much as now. But at the peak back in April, May and some of June, most folks were sick with other types of respiratory ailments. Now I am guessing that most of those showing symptoms are in fact covid, but they are also now testing anyone who wants a test - symptomatic or not.
 
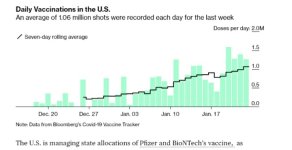
Escorted another older family friend getting her Covid vaccine today. In and out in about 25 minutes. Chatting with staff they said they were having trouble staffing the coliseum across town which started vaccines last week. The staff had observed and copied the location I’ve taken people to. One might want to find the facility that’s been doing vaccines the longest in you area if your state gives you a choice of locations. Hate to hear people are sitting in lines for many hours and not getting a vaccine. They hadn’t had any cancellations today ( 1:00 o’clock) which would have opened up an opportunity for someone else ( caregiver) to get an unscheduled vaccine. Really great people putting shots in arms .
 
... BTW, neither I nor my wife have been tested)...

The testing thing kind of cracks me up. Today, I just had my (at least) sixth test(have to have a negative test for the shoot I'm booked on this coming week) and I have friends that have had even more over the last few months, all for shoots(while we are classified under "essential businesses", we are hardly doing truly essential, life saving work). But most medical personnel receive no tests. My GF, who is a paramedic, has not had a single test, yet.
 
The testing thing kind of cracks me up. Today, I just had my (at least) sixth test(have to have a negative test for the shoot I'm booked on this coming week) and I have friends that have had even more over the last few months, all for shoots(while we are classified under "essential businesses", we are hardly doing truly essential, life saving work). But most medical personnel receive no tests. My GF, who is a paramedic, has not had a single test, yet.

My wife is a therapist at a SNF and gets tested twice a week... and has been since at least October. Before that it was once a week. It’s certainly not universally true that medical staff aren’t being tested... it’s the norm here.
 
Back
Top